


Pseudoexfoliation Syndrome: What It Means for Eye Pressure, Glaucoma and Cataract Surgery
Blurred vision and extra glare from headlights at night are common signs of cataract, one of the two main eye problems linked to pseudoexfoliation syndrome. The other is a rise in pressure inside the eye, which may cause no symptoms at first. Pseudoexfoliation itself is often underdiagnosed, as its early stages can be missed during an eye examination. Because raised eye pressure can lead to glaucoma, pseudoexfoliation care often forms part of glaucoma assessment and management.
Quick Overview
- Pseudoexfoliation syndrome is an age-related condition in which white-grey flakes of fibrous material build up on the lens and other tissues at the front of the eye.
- The flakes can clog the eye’s drainage tissue, which raises intraocular pressure and can damage the optic nerve over time.
- Age is the main risk factor, and the condition is more common in some populations, including Indigenous Australians.
- Pressure checks, eye drops, laser therapy or surgery may be used to manage raised eye pressure, depending on your individual situation.
The sections below explain how the condition develops, how it is found and how it affects treatment.
What Is Pseudoexfoliation Syndrome?
Pseudoexfoliation syndrome is a condition in which fine, fibrous material collects on anterior segment structures, the tissues at the front of the eye. The material is most often seen on the anterior lens capsule, the thin clear layer covering the lens, and along the pupillary margin, the inner edge of the coloured iris.
The material forms when the extracellular matrix, the supporting framework between cells, is not built or broken down in the usual way. The lens epithelium, iris, ciliary body and trabecular meshwork are all thought to produce it. The flakes contain basement membrane components, elastic fibre proteins and blood proteins, which suggests inflammation plays a part. Over time, the deposits spread across the lens capsule and other ocular tissues.
Why Does Pseudoexfoliation Raise the Risk of Glaucoma?
The material builds up in the trabecular meshwork, the drainage tissue in the angle of the eye, and makes it harder for fluid to leave. The resulting elevated IOP can damage the optic nerve. Glaucoma caused this way is called pseudoexfoliation glaucoma, a type of secondary open-angle glaucoma.
Pseudoexfoliation is the most common identifiable cause of secondary open-angle glaucoma, and it raises the risk of developing glaucoma. Not everyone with pseudoexfoliation will develop glaucoma, although around half of patients are eventually diagnosed with it. Compared with primary open-angle glaucoma, the secondary glaucoma it causes tends to show higher intraocular pressure, wider pressure swings, more advanced optic nerve damage at diagnosis and faster glaucoma progression. This makes it one of the more clinically complex forms of glaucoma to treat.
The drainage tissue in these eyes often carries extra pigment in a patchy pattern, which is different from the more even spread seen in pigment dispersion syndrome. Pigment can also be released from the iris pigment epithelium as the iris rubs against the flaky anterior lens. Optic nerve damage from glaucoma cannot be repaired once it occurs.
Who Is More Likely to Develop Pseudoexfoliation?
Age is the strongest of the known risk factors, and the condition is uncommon before 50. Rates vary widely between countries and ethnic backgrounds, and the underlying factors are not fully understood.
In Australia, reported rates range from about 1% to 4.7%, depending on the study. Among Indigenous Australians aged over 60, rates of up to 16% have been recorded, compared with about 3% in non-Indigenous Australians of the same age. These Australian figures come from studies completed more than a decade ago, so current rates may differ.
Pseudoexfoliation is a multifactorial disorder, meaning no single cause has been identified. Previous intraocular surgery may also play a part, as it can disturb the barrier that keeps blood proteins out of the fluid inside the eye.
How Is Pseudoexfoliation Found During an Eye Examination?
 Pseudoexfoliation is diagnosed through a clinical examination with a slit lamp microscope, usually after drops are used to widen the pupil. On the lens, the flakes often form three zones: a central disc, a clear ring and an outer band.
Pupillary dilation is often weaker in these eyes because the material builds up in the iris stroma and makes the tissue less elastic. Your ophthalmologist also examines the drainage angle, a test called gonioscopy, which can show that the angle is narrower than usual. The narrowing is thought to come from zonular weakness, where the fine fibres holding the lens loosen and allow anterior lens displacement. Deposits can also collect on the corneal endothelium, the inner cell layer of the cornea.
Six-monthly pressure checks are recommended for early diagnosis of any pressure rise, because these eyes carry a high risk of glaucoma development.
What Does Pseudoexfoliation Mean for Cataract Surgery?
Cataract surgery is often more complex in eyes with pseudoexfoliation. The pupil may not widen fully, and weak zonules can let the lens move during surgery, which raises the risk of capsular rupture, a tear in the thin bag that holds the lens.
A review of cataract surgery complications identified five factors linked to problems in these eyes: a shallow anterior chamber, a denser cataract, higher eye pressure before surgery, a raised inflammation marker in the blood and flakes in both eyes. To plan for lens instability, your ophthalmologist may use a capsular tension ring, a small device that supports the lens capsule.
Postoperative complications reported after cataract extraction in these eyes include swelling of the cornea, loss of cells from the corneal endothelium, and later shifting of the lens implant. Surgical risks may be lower when the condition is at an earlier stage, so your ophthalmologist may suggest having cataract surgery earlier.
How Is Pseudoexfoliation Glaucoma Treated?
No approved treatment targets the pseudoexfoliation material itself, so glaucoma treatment focuses on lowering intraocular pressure. Options include eye drops, laser therapy and surgery, and treatment often needs to be stepped up over time to keep the pressure under control.
Prostaglandin analogues are commonly used as first-line drops, as they help fluid leave the eye through a second drainage route. A single type of drop is often not enough in this form of glaucoma, because starting pressures tend to be higher.
Selective laser trabeculoplasty is a form of laser surgery that treats the trabecular meshwork to improve drainage, and it can be used first or alongside drops. The laser energy is adjusted in these eyes because heavier pigment can make pressure spikes more likely, and the treatment may need repeating as its effect fades.
When drops and lasers do not control the pressure, surgical intervention may be needed. Options include minimally invasive glaucoma surgery for mild to moderate glaucoma, and trabeculectomy, a form of glaucoma surgery that creates a new drainage channel. Glaucoma patients with pseudoexfoliation are more likely to need surgery, and inflammation after surgery is more common, so surgical management calls for careful planning. Individual outcomes vary, and your ophthalmologist will discuss which approach suits your eyes.
Is Pseudoexfoliation Syndrome Linked to Other Health Conditions?
Pseudoexfoliation is increasingly recognised as a systemic disorder. The same material has been found in the heart, lungs, liver, kidneys and blood vessel walls, a pattern described as systemic pseudoexfoliation syndrome.
Links with heart and circulation conditions have been reported, including high blood pressure, angina, heart attack and stroke. Proposed reasons include deposits in vessel walls causing increased vascular resistance and endothelial dysfunction in the lining of blood vessels. An association with abdominal aortic aneurysm has been reported, although findings are inconsistent. Whether pseudoexfoliation contributes to cardiovascular disease, or simply occurs alongside it, is still unclear.
These findings have clinical implications beyond the eye. Appropriate patient care includes telling your ophthalmologist about any heart, blood pressure or circulation conditions you have.
Pseudoexfoliation Assessment and Treatment at Armadale Eye Clinic
 Because pseudoexfoliation can raise eye pressure and weaken the fibres that hold the lens, it affects both glaucoma care and cataract surgery planning. At Armadale Eye Clinic, our ophthalmologists use optical coherence tomography and visual field testing to assess the optic nerve and monitor for glaucoma progression. Treatment options at the clinic include eye drops, selective laser trabeculoplasty and minimally invasive glaucoma surgery, which can be combined with cataract surgery in suitable cases. To arrange an assessment, please call us on (03) 9070 5753.
Frequently Asked Questions
Is exfoliation syndrome the same as pseudoexfoliation syndrome?
Yes, the two names are used for the same condition, and the related glaucoma appears in medical literature as exfoliation glaucoma, exfoliative glaucoma or pseudoexfoliative glaucoma. True exfoliation syndrome is a different condition, in which the outer layers of the lens capsule split away after exposure to heat or infrared radiation. Glaucoma is uncommon with true exfoliation syndrome.
If pseudoexfoliation syndrome affects one eye, will the other eye be affected too?
Yes, it can. The condition often shows in one eye first, and in some cases it later becomes visible in both eyes. Tissue studies have also found subtle changes in the second eye before any flakes can be seen, which is why pseudoexfoliation is thought to affect both eyes unevenly.
Does pseudoexfoliation syndrome run in families?
Genetics play a part. Changes in a gene called LOXL1, which is involved in building and stabilising elastic fibres, are a significant genetic risk factor. Non-genetic factors also have a role, so carrying these gene changes does not by itself mean you will develop the condition.
Does pseudoexfoliation syndrome cause dry eyes?
Dry eye is more common in eyes with pseudoexfoliation, with lower tear production and faster tear break-up reported. This matters for glaucoma treatment, as preservative-free eye drops may be preferred when the eye surface is dry.
Can cataract surgery lower eye pressure in pseudoexfoliation syndrome?
Cataract surgery may lower intraocular pressure somewhat in eyes with pseudoexfoliation. Signs of the condition can remain on other ocular structures after the lens is replaced, although they may be subtle. For this reason, slit lamp reviews and pressure checks continue after cataract surgery.
Can lifestyle changes help with pseudoexfoliation syndrome?
Smoking, high caffeine intake, alcohol and low folate or vitamin B12 levels have been linked to pseudoexfoliation, as has long-term ultraviolet exposure. Stopping smoking, limiting caffeine and alcohol, and wearing UV-protective sunglasses may be reasonable steps. Research has not yet confirmed that these changes alter the course of the condition.
Any surgical or invasive procedure carries risks. Before proceeding, you should seek a second opinion from an appropriately qualified health practitioner.
References
https://glaucoma.org.au/what-is-glaucoma/glaucoma-treatments/laser-treatment
https://eyeandear.org.au/health-professionals/clinics-services-partnerships/glaucoma-unit/

Multifocal intra-ocular lenses offer the opportunity to have cataract surgery and have great vision for distance, intermediate and near. There are a few golden rules Read more

We all develop presbyopia when we get to between 45-50 yeas of age. Presbyopia is the loss of the ability to focus up near. This Read more

The eye is an amazing organ with multiple parts all working together to receive light, convert it to neural signals, and send this signal onwards Read more

Unfortunately, no, long sightedness is not exactly as simple as being the opposite of short sightedness. People with long sightedness can in fact often still Read more
 A lamellar macular hole is a gap that extends only partway through the fovea. Tissue is lost from the inner layers of the retina, and in some eyes, the outer retinal layers are also affected. Unlike
 Surgery is typically considered when vision is declining, distortion is getting worse, or scans show the hole is changing. In a vitrectomy, the vitreous gel is removed, any epiretinal proliferation or membrane is lifted, and the thin inner lining of the retina may be peeled to relieve traction.

 Your sight in the operated eye will be blurred at first. The bubble sits across your line of view, and you may see a dark, wobbling edge that sinks lower each week as the gas shrinks. While the bubble is present, it

 As the pressure continues, the vessels can leak or bleed, and doctors describe the severity in steps. Mild changes come first. Moderate retinopathy adds small bleeds in the retina (retinal haemorrhages), cotton-wool spots (soft white patches where blood flow has dropped) and hard exudates (small fatty deposits that leak from the vessels).
 The foundation of managing either retinopathy is treating the condition behind it, because the eyes tend to follow the health of the body. For raised blood pressure, that means bringing systemic blood pressure control through lifestyle and, where needed, blood pressure medicines prescribed and reviewed by your GP. For diabetes, it means steady blood sugar, along with blood pressure and cholesterol within target ranges.

 This is worth being clear about. There is no cure for macular degeneration, and
 Aids help you use your sight, but protecting the vision you have still matters.

 In younger eyes, the vitreous gel is firmly attached to the retina, including the macula, the central part responsible for fine detail. As the years pass, this gel naturally becomes thinner and more watery. It gradually separates from the back of the eye in a process called posterior vitreous detachment, something nearly everyone experiences to some degree.
 Very small holes caught early are sometimes simply monitored rather than treated immediately. For holes affecting vision more significantly, vitrectomy surgery is the standard surgical procedure. Performed under local anaesthetic, this surgery removes the vitreous gel responsible for the traction and replaces it with a gas bubble.
 A thorough eye examination, including optical coherence tomography where needed, gives you clarity on what is happening and what comes next. The sooner a macular hole is assessed, the more options generally remain open. The team at Armadale Eye Clinic can examine your retina in detail, explain your results clearly, and walk you through the right next steps based on your individual situation.

 Your eye produces a clear fluid called aqueous humour. This fluid nourishes the lens, cornea, and other internal structures. It travels through each part of the eye that has no blood supply, then drains out through tiny channels at the front. The fluid inside the eye is constantly being made and drained. When those two processes stay in balance, pressure inside the eye stays stable.
 Eye pressure, or IOP, is measured using tonometry. There are several ways to measure eye pressure at a comprehensive eye examination. The most reliable method is contact tonometry, where a small instrument gently touches the surface of your numbed eye and measures the force needed to flatten a tiny area of the cornea. Non-contact tonometry, which most people know as the air puff test, works on the same principle without touching the eye.
 High eye pressure feels like nothing. There is no sensation, no blurry vision in most cases, and no warning sign you can notice yourself. That is what makes regular monitoring so important. Glaucoma caught early is far more manageable, and the earlier elevated pressure is identified, the more options are available to prevent vision loss.

 Macular degeneration is a condition that affects the macula, which is the central part of the retina. The retina is the light-sensitive layer at the back of the eye that sends visual information to the brain.

 Even though this article focuses on dry macular degeneration, it is

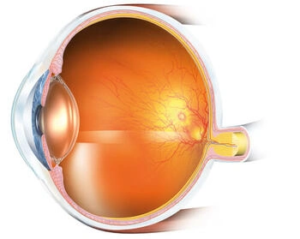 How Uveitis Develops Inside the Eye
 An anti-inflammatory approach emphasises balance and nutrient support.
 While diet alone cannot prevent uveitis, thoughtful choices may support how uveitis is treated and respond over time. For uveitis patients, awareness of triggers and supportive habits can reduce disruption. An anti-inflammatory diet can complement care plans and support symptom awareness. Diet remains one part of a broader strategy.

 Extended hours at a computer, tablet, or phone can contribute to eye strain, which may make your
 Comprehensive eye assessments allow an eye doctor to examine your eyes in detail. These tests can detect:
 If you notice ongoing or sudden blurry vision, seeking guidance can help you understand what is contributing to the change and what approaches may support clearer,